❌

Reading view

The DEA Wants To Turn 7-OH Consumers Into Criminals

Kratam-2-science-products | Puntasit Choksawatdikorn/Dreamstime

The federal drug police want to turn consumers of certain concentrated kratom-derived products into criminals while leaving traditional kratom leaf products outside the ban. Before exposing adults to arrest and prosecution, the feds owe them a scientific explanation for that distinction.

On October 14, the Drug Enforcement Administration (DEA) announced its intent to temporarily place 7-hydroxymitragynine (commonly called 7-OH) and mitragynine pseudoindoxyl—above specified thresholds—in Schedule I. Schedule I is the category for drugs that the agency thinks have "no currently accepted medical use" and "a high potential for abuse." A scheduling order could be issued on or after November 13.

The DEA already classifies mitragynine pseudoindoxyl as a Schedule I substance regardless of concentration. The proposal would ease that restriction by introducing thresholds—while imposing new Schedule I restrictions on 7-OH under the same criteria.

The Food and Drug Administration (FDA) and the Department of Health and Human Services (HHS) have supported the DEA's move, and HHS supplied the proposed thresholds. Under the temporary scheduling provision of the Controlled Substances Act, the DEA must consider HHS's comments but need not follow its recommendations. Congress gave a law-enforcement agency the authority to decide which drugs individuals may consume.

The ordinary scheduling process gives health officials more authority: HHS's scientific and medical findings bind the DEA, and its recommendation against control prevents the agency from proceeding. But temporary scheduling lets the DEA bypass those requirements when it determines a substance poses an imminent hazard to public safety.

Congress should never have given federal drug police that power. Having done so, it should at least demand compelling evidence before they exercise it.

Kratom comes from a Southeast Asian plant whose principal alkaloid is mitragynine. Its leaves contain trace amounts of 7-OH. Manufacturers also sell concentrated 7-OH products and products containing the related compound, mitragynine pseudoindoxyl.

Millions of Americans use kratom or kratom-derived products. A 2022 review cited an estimate of 2.1 million U.S. users in 2020. In a survey of 2,798 users, 91 percent reported using it for pain and 41 percent said they use it to reduce or stop opioid use. In a letter to HHS, nine military veterans described using 7-OH to manage pain and symptoms of post-traumatic stress disorder and to move away from other opioids and from alcohol. They warned that banning it could drive them back to more dangerous drugs.

These reports describe benefits that warrant further study and needs that will persist after a ban.

Concentrated 7-OH products deliver a potent alkaloid without requiring consumers to ingest large amounts of kratom leaf. 7-OH is significantly more potent than mitragynine in activating the opioid receptors involved in pain relief. Researchers still need to determine how its benefits and risks compare across different human doses.

The DEA's proposed criminal controls hinge on concentration and composition. The concentration threshold is 1 milligram per gram of solid material or 1 milligram per milliliter of liquid, calculated for the two covered substances combined. Products would also trigger controls if the mitragynine-to-covered-substances ratio fell below 100 to 1.

Consider a tablet containing 15 milligrams of 7-OH, a strength advertised by some sellers. If the tablet weighs one gram, its concentration exceeds the limit fifteenfold. Diluting the same 15 milligrams into a product weighing 15 grams brings it to the concentration limit. Consuming the entire product still delivers the same dose. It would also need at least 1,500 milligrams of mitragynine to avoid the separate ratio restriction.

Adding bulk changes the concentration but does not change the amount of 7-OH consumed. These calculations tell us nothing about whether that dose is effective or safe.

The DEA acknowledges that controlled trials have not established safe consumption limits or standardized dosing for concentrated 7-OH products. Neither DEA nor HHS has determined that below-threshold products are safe.

In a public comment submitted to HHS in July, I urged officials to obtain the human evidence needed to justify a threshold before setting one. Animal studies can reveal hazards, including dependence and respiratory depression, but they cannot, by themselves, identify a scientifically defensible cutoff for human consumption.

Officials may intend these thresholds to distinguish traditional kratom from concentrated products. What evidence shows that crossing that boundary justifies criminal penalties? 

The DEA also owes consumers an accounting of what prohibition could do to them. People seeking relief from pain or withdrawal will still need it after a ban. Some may abandon these products, while others may turn to illicit sellers or switch to other opioids. Criminalizing those choices could make them more dangerous.

Misleading labels, contamination, dependence, and drug interactions warrant attention. Accurate labeling, independent testing, age restrictions, and enforcement against fraud can address several of these concerns. Before resorting to criminal penalties, the DEA should explain why those measures would be inadequate.

We already know how difficult it is to verify a drug's identity, strength, and purity in an illicit market. Creating another prohibited product will give that market another opportunity.

Autonomous adults should be free to decide which substances they consume and which risks they accept. The DEA proposes taking that choice away even as it acknowledges major gaps in the medical evidence. Before the drug police turn more consumers into criminals, they should at least demonstrate how doing so will make those consumers safer.

The post The DEA Wants To Turn 7-OH Consumers Into Criminals appeared first on Reason Magazine.

  •  

Mental Illness Doesn't Cancel Your Right to Say No

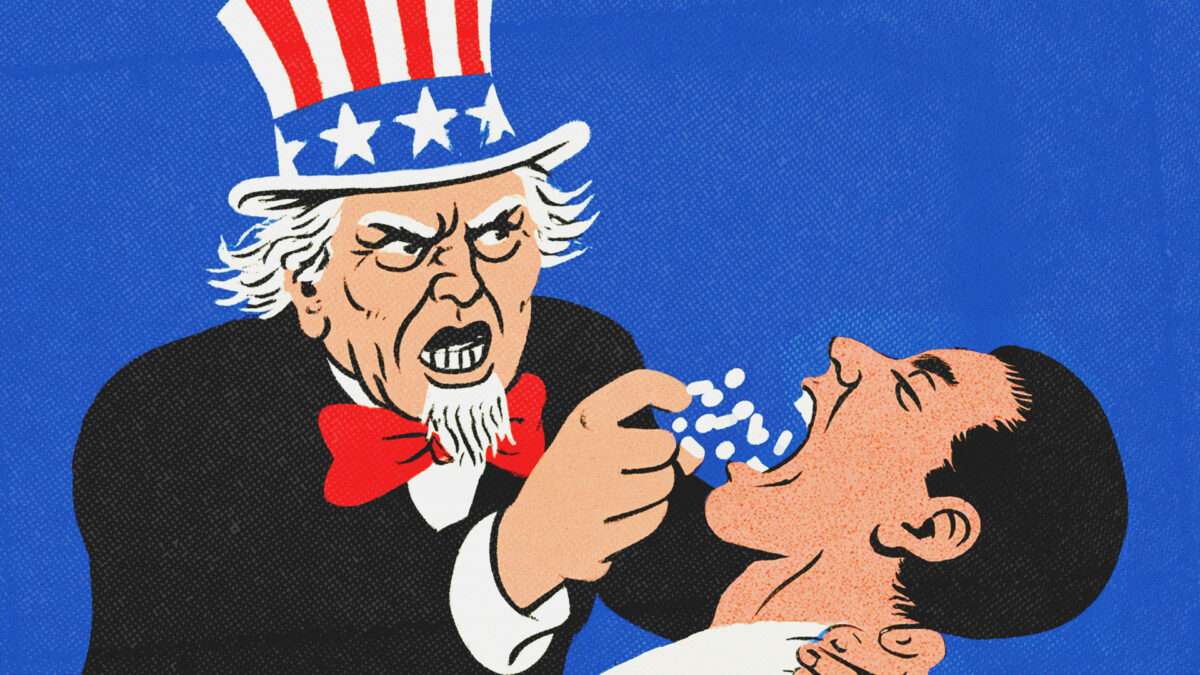
Uncle Sam force feeding a man some pills | Midjourney

If a treatment can improve your health, does that give the government the right to force it onto you? Should the state compel people with diabetes to take insulin, patients with hypertension to take their medications, or people with obesity to lose weight?

Most Americans would recoil at such proposals. Yet when it comes to people diagnosed with psychiatric disorders, many people seem willing to make an exception.

A physician who administers treatment to a competent adult against the patient's will violates one of medicine's most fundamental ethical principles: informed consent. Why should that principle carry less weight when the doctor is a psychiatrist? Yet in a recent City Journal article, Stephen Eide and Valerie Franchitti of the Manhattan Institute argue that public support for involuntary psychiatric treatment reflects a welcome recognition of its potential benefits.

Strangely, the article entirely avoids the concept of informed consent. Where it acknowledges any limitations to involuntary treatment at all, it considers only the possibility that coercive treatment may increase stigma against mental illness.  

But the more fundamental objection is liberty. A psychiatric diagnosis does not extinguish your right to control your body. Competent adults have the right to decide what substances they consume, which medical treatments they accept, and what risks they take, even when others consider their choices unwise or self-destructive. As the psychiatrist Thomas Szasz wrote in 1997, "I oppose involuntary psychiatric interventions not because I believe that they are necessarily 'bad' for patients but because I oppose using the coercive apparatus of the state to impose psychiatric relations on persons against their will."

Eide and Franchitti write, "The public is right to suspect that involuntary treatment can be effective." They cite data from the New York State Office of Mental Health showing substantial reductions in hospitalization, incarceration, homelessness, substance abuse, and suicide attempts following enrollment under Kendra's Law, which mandates outpatient psychiatric treatment. Yet these data do not establish that coercion caused those improvements. Participants also received increased access to psychiatric services, case management, and other support. Without adequately separating the effects of those services from the effects of coercion itself, the reported improvements cannot establish that compulsory treatment was responsible.

The authors also justify involuntary psychiatric treatment by citing subway attacks, mass shootings, and other violent incidents. But there is a fundamental difference between holding people accountable for violating others' rights and confining them because they might become dangerous. Communities can enforce laws against assault, trespassing, and public nuisance without criminalizing homelessness or mental illness.

Moreover, involuntary commitment to a psychiatric hospital or rehabilitation facility—sometimes for prolonged periods—deprives people of their liberty without a criminal conviction. Although civil commitment involves judicial procedures and opportunities for review, continued confinement may depend heavily on mental health professionals' assessments of whether patients meet release criteria. As Szasz warned, coercive psychiatrists can thus function as "judges and jailers not physicians and healers."

Severe mental illness can impair decision-making, sometimes profoundly, but diagnosis and incapacity are not the same. Even among psychiatric inpatients housed for severe mental illness, a meta-review of the research at BMC Psychiatry shows, most retain the capacity to make treatment decisions. Outside of hospitalized patients, decision-making capacity is even higher. 

The legal scholar Elyn Saks, who has lived with schizophrenia, brings both personal experience and academic expertise to the debate over involuntary psychiatric treatment. Having experienced involuntary hospitalization, physical restraints, and forced medication, Saks has questioned the assumption that mental illness justifies overriding patients' wishes. In her book Refusing Care she examines the ethical and legal problems posed by involuntary hospitalization, forced medication, and physical restraints. Saks and the psychiatrist Dilip Jeste have also reviewed empirical research on decision-making capacity among people with psychiatric and substance use disorders, analyzing how capacity varies among individuals and how clinicians can assess and enhance patients' ability to make informed decisions. 

Though the medical field has developed structured interviews with standardized scores for mental incapacity, doctors can disagree on assessment. Mental capacity is also decision-specific and time-specific, not a permanent status attached to a diagnosis. That same BMC Psychiatry review of the literature describes the impairments seen in psychosis as "temporal, identifiable, and responsive to interventions," such as presenting information in simpler terms. 

Even when incapacity can be established, we must adhere to the principle of least restrictive intervention. Any intervention must be justified by the circumstances, limited to what is necessary, and designed to preserve as much individual freedom as possible. Compulsory treatment takes different forms, each imposing distinct restrictions on individual liberty. Assisted outpatient treatment allows people to remain in the community but subjects them to a court order governing treatment. Involuntary inpatient commitment deprives people of their physical liberty through hospitalization, while forced medication goes further by overriding bodily autonomy. So impaired decision-making capacity does not automatically justify confinement, let alone forced medication.

Medication can reduce psychotic symptoms, and some psychiatric patients who initially refuse treatment later believe it helped them. But evidence that medication works is not the same as evidence that compulsion produces better outcomes than voluntary treatment, particularly when a person's decision-making capacity may improve as an acute episode subsides.

In 2024, a scoping review in the journal Psychiatry, Psychology and Law found mixed evidence of benefits and harms from involuntary inpatient treatment. Patients admitted involuntarily often experienced improvements in symptoms and functioning, but they also tended to enter treatment with more severe illness, making it difficult to determine how much of the improvement resulted from compulsory intervention itself. Involuntary admission was also associated with higher financial costs and worse patient experiences, including feelings of coercion, loss of freedom, and lower satisfaction. In 2018, The Canadian Journal of Psychiatry published a systematic review of coercive measures; it found that patient experiences were predominantly negative and frequently involved adverse consequences. Overall, no consistent evidence shows that involuntary treatment itself causally improves outcomes, although it unquestionably restricts patients' freedom and imposes costs on taxpayers.

These concerns are compounded by a health care system that financially incentivizes psychiatric overdiagnosis and overmedication, regardless of whether additional interventions yield commensurate benefits for patients.

The difficult case arises when a person genuinely cannot reason about treatment options or communicate an informed choice, and when delaying intervention creates an immediate risk of harm. In such cases, the ethical principle should be the same as elsewhere in medicine: Temporary treatment may be justified when informed consent cannot be obtained, using an advance directive or surrogate when available, and only to the minimal extent necessary to manage the emergency and restore the patient's ability to decide. A credible, imminent threat to another person presents a separate public-safety justification for state intervention. But even support for those types of emergency interventions is not the same as support for broad, long-term involuntary psychiatric treatment based on supposed mental incapacity.

City Journal frequently advocates free markets, individual liberty, and limits on government intervention. Yet these writers appear willing to grant the state considerable authority over people's medical decisions without adequately distinguishing those who lack decision-making capacity from those who retain it. If we distrust government officials to make economic decisions for us, why should we trust them to make decisions about our bodies and medical care?

The post Mental Illness Doesn't Cancel Your Right to Say No appeared first on Reason Magazine.

  •  

The Government Doesn't Know What's Best for You. Why Let It Decide What You Should Eat?

Gloved hand of Uncle Sam assembling food like eggs and yogurt on a table | 50jb/Dreamstime/USDA/HHS/Fatima Ruiz

Governments have spent decades issuing dietary guidelines, sponsoring public health campaigns, and encouraging consumers to cut back on sugary, salty, and fatty foods. Now they're moving beyond persuasion and adopting more aggressive measures to influence what people eat.

In an October 8 article titled "Nagging People to Eat Healthily Does Not Work," The Economist describes a growing international movement to tax unhealthy foods, restrict advertising, require warning labels, and regulate how supermarkets display and promote their products. Such measures are needed, officials argue, because the earlier approach failed to curb rising obesity rates.

The Economist notes, for example, that from 1992 through 2020 Britain adopted 14 national strategies to reduce obesity, comprising 689 individual policies. Most of these sought to educate consumers about healthy eating or improve access to healthier foods. Yet England's obesity rate doubled over roughly the same period.

The article treats the rise in obesity as evidence that these efforts failed, and its framing implies that governments need to go further. But the fact that obesity increased despite these initiatives doesn't tell us whether they were effective. (After all, obesity might have increased even faster without them.) More importantly, it doesn't follow that more intrusive interventions will improve health outcomes.

The Economist article cites a study that attributes Mexico's reductions in calories, added sugar, and saturated fat sold to mandatory warning labels. But these measures reflect changes in food purchases and product formulations, not demonstrated improvements in health. The article provides no evidence that the labeling requirements have reduced obesity, diabetes, cardiovascular disease, or mortality.

And who decides which foods should carry warning labels, face higher taxes, or be restricted in where retailers can display them? The government has a poor track record in providing nutritional advice.

Terence Kealey, Bautista Vivanco, and I wrote a Cato Institute article earlier this year examining the history of federal dietary guidelines. We traced how officials adopted dietary recommendations grounded in scientific theories that were contested from the outset and inadequately supported by experimental evidence.

In 1977, the Senate Select Committee on Nutrition and Human Needs issued Dietary Goals for the United States, urging Americans to reduce fat and cholesterol intake while increasing carbohydrate intake. The recommendations reflected the prevailing hypothesis that dietary fat and cholesterol were major causes of cardiovascular disease.

But the evidence was far from conclusive. Researchers had challenged the correlations underpinning the hypothesis, and randomized trials available at the time had failed to show a mortality benefit from reducing dietary fat. The American Medical Association warned in 1977 that the evidence supporting universal dietary goals was inconclusive and that the recommendations could have harmful consequences.

Nevertheless, federal officials pressed forward.

For decades, government dietary guidance encouraged Americans to limit cholesterol-rich foods, including eggs and shellfish. It wasn't until 2015 that the Dietary Guidelines Advisory Committee concluded that dietary cholesterol was no longer a nutrient of concern for overconsumption.

Meanwhile, the campaign against dietary fat coincided with—and may have contributed to—significant shifts in American eating habits. According to the U.S. Department of Agriculture (USDA), from 1970 through 2003 per capita availability of grains rose by 43 percent, while added fats and oils rose by 63 percent. A separate USDA report found that per capita consumption of whole milk declined by 70 percent over that period, while consumption of lower-fat and skim milk increased by 140 percent. The USDA attributed this shift to warnings about saturated fat. Even after scientists raised concerns about trans fats, federal dietary guidelines continued to favor margarine over butter. Some margarines contained partially hydrogenated oils, which the Food and Drug Administration (FDA) later determined were no longer generally recognized as safe because of their cardiovascular risks.

These trends don't prove that government dietary advice caused Americans to change their diets. But government recommendations can influence what manufacturers produce and what consumers buy. When these recommendations are wrong, the consequences can be widespread.

Nutritional science is complex, and scientific consensus can shift. Government officials are no less susceptible to error than anyone else. Yet when the government endorses a particular dietary theory, its recommendations carry authority that can discourage competing approaches and magnify the consequences of mistakes.

The latest federal dietary guidelines illustrate this problem. The Trump administration's 2025–2030 guidelines introduced a new food pyramid that places greater emphasis on proteins and fats while discouraging refined carbohydrates. Whatever the merits of those changes, the reversal demonstrates how dramatically official dietary recommendations can shift.

The uncertainty doesn't end with fats and carbs.

Consider the growing campaign against ultra-processed foods. Numerous observational studies link higher consumption of these products to obesity, cardiovascular disease, diabetes, and other adverse health outcomes. Yet researchers have not yet determined precisely which ingredients, additives, processing methods, or combinations of these factors account for many of those associations, or at what exposure levels.

Nor is there universal agreement on what constitutes an "ultra-processed" food in the first place. As Kealey, Vivanco, and I pointed out in another Cato article, the widely used NOVA classification system places a broad range of products in the ultra-processed category, including some fortified cereals and breads that provide valuable nutrients. Researchers have struggled to classify certain foods consistently. A 2025 systematic review identified six different systems for classifying highly processed foods, each with its own criteria.

Even the federal government recognizes the problem. In July 2025, the Department of Health and Human Services (HHS), the FDA, and the USDA announced plans to develop a uniform definition of ultra-processed foods. Their request for information acknowledged that existing classifications can include nutritious foods such as whole grains and yogurt. In August 2026, HHS announced that the agencies had submitted a proposed definition for final review.

Some ultra-processed foods may indeed pose health risks. But broad categories can obscure important differences among products, and observational associations alone cannot tell us which ingredients or processing methods cause adverse health outcomes.

The Economist article reports that Britain is considering a system that would require supermarket chains to meet government-defined nutritional targets across their entire sales. Rather than merely informing customers about nutritional content, the government would make retailers responsible for altering the composition of what consumers buy. Supermarkets could comply by promoting certain foods, discouraging others, or pressuring manufacturers to reformulate their products.

Government nutrition authorities would thus have considerable power to influence what supermarkets sell and what consumers buy. If their nutritional assumptions prove mistaken, the consequences could affect millions of consumers.

Consumers benefit from accurate information about the ingredients and nutritional content of the foods they buy. But providing information is different from using government power to manipulate prices, restrict advertising, or pressure retailers to change what they sell.

Moreover, people have different nutritional needs, preferences, and attitudes toward risk. Some may willingly trade potential long-term health benefits for convenience, affordability, or the simple pleasure of eating foods they enjoy. These are choices individuals are entitled to make for themselves.

That raises a more fundamental issue. Even if officials had perfect knowledge of nutrition, why would that entitle them to dictate the dietary choices of competent adults?

Most people would likely oppose the government compelling patients with hypertension to take their medications, forcing sedentary adults to exercise, or prohibiting people from engaging in recreational activities that pose health risks. Why should eating be any different?

Adults should be free to seek dietary advice from physicians, nutritionists, researchers, or anyone else they trust—and to decide whether to follow it. They should also be free to disregard that advice, even if that might increase their health risks.

The post The Government Doesn't Know What's Best for You. Why Let It Decide What You Should Eat? appeared first on Reason Magazine.

  •  
❌