When we think of Greek mathematics, we think of Euclid, Archimedes and Apollonius of Perga: elegant proofs and general rules. Alongside that tradition ran a humbler one, which rarely makes it into textbooks. It was maths for getting a job done, and a new study argues that the people who practised it leaned heavily on […]
In the previous article, I discussed general aspects of the political testament left by the greatest science communicator of the 20th century: Carl Sagan (1934–1996). I showed that his Epicurean worldview leads him to portray life on Earth as the result of an extremely ephemeral convergence of causes, that humanity must artificially sustain to prevent our species from going extinct. This maintenance requires a global pact governed by scientists. Scientists are special beings because they are, supposedly, the only ones who strive to foresee catastrophes. Sagan artificially divides humanity into two groups: Enlightenment atheists who embrace science, and religious obscurantists who reject it. Therefore, for the species to survive, the former must prevail over the latter.
In his political testament, Billions and Billions (1997), the causes he champions are environmentalism and abortion. Today, I aim to show that these two causes are, in fact, one and the same: Neo-Malthusianism.
It is easy to prove that Carl Sagan was a Neo-Malthusian. Here is what he says in the chapter “The Persian Chessboard”: “Exponentials are also the central idea behind the world population crisis. […] As the English clergyman Thomas Malthus pointed out in 1798, a population increasing exponentially— Malthus described it as a geometrical progression— will outstrip any conceivable increase in food supply. No Green Revolution, no hydroponics, no making the deserts bloom can beat an exponential population growth. There is also no extraterrestrial solution to this problem. […] Even if it were possible to ship everybody on Earth off to planets of distant stars on ships that travel faster than light, almost nothing would be changed— all the habitable planets in the Milky Way galaxy would be full up in a millennium or so.”
There is no caveat regarding the error of Malthus’s prophecy, nor any consideration of the inhumanity of his recommendations. Malthus is portrayed as a scientific hero. And, with surprising dogmatism, Sagan dismisses—without argument—the idea that technological improvements could solve the food problem. Mind you: Sagan takes it for granted that, even on different planets, humans would continue to procreate exponentially, when fertility rates historically differ even between rural areas and the urban middle class! And a thousand years is far too short a timeframe for humanity, with all its astronomical development, to solve a problem!
Instead of openly proposing that the poor be denied charity, like old Malthus, Sagan proposes birth control and technological apartheid. Instead of helping the poor, then, we must prevent them from being born and deprive them of technology—except for birth control technology, which, it seems, is entirely immune to causing unforeseen environmental damage. Moreover, while old Malthus had England’s poor in mind, Sagan broadens his scope to include the world’s poor nations—nations that keep growing and adopting technology, something supposedly responsible for significant environmental damage.
Were he to state these things explicitly, he would clearly appear as a villain. Thus, in the same chapter, the issue of birth control is wrapped in the language of humanitarianism and feminism: “There is a well-documented worldwide correlation between poverty and high birthrates. In little countries and big countries […] in almost all these cases, exponential population growth slows down or stops when grirfcling poverty disappears. This is called the demographic transition. It is in the urgent long-term interest of the human species that every place on Earth achieves this demographic transition. […] One of the central issues in the world population crisis is poverty.”
Correlation does not imply causation, yet Sagan argues as if it did. People are not poor because they have children; rather, they have children because the cost of raising them is low and is offset by the utility of their labor: in an underdeveloped setting, all farmers need to provide their children is food—which the land itself yields—and within a few years, the child begins to assist the family with work. A sterile couple would not become wealthy simply by virtue of having no children; they would merely save on food that might well otherwise rot, while failing to multiply their workforce. If matters stood as Sagan claims, sterility would be a blessing in agrarian societies, yet reality demonstrates the opposite.
He continues: “The exceptions to the demographic transition are interesting. Some nations [which he does not name] with high per capita incomes still have high birthrates. But in them, contraceptives are sparsely available, and/or women lack any effective political power. It is not hard to understand the connection.” At no point in the book does he explain what criteria must be met to say that women possess real political power within a society. This is regrettable, given his assertion that women held such power during the Pleistocene (!!) but do not today. Thus, since Sagan cites no sources for this information, one can only conclude that he is fabricating a series of pretexts to advocate for contraception, tailored to whatever reality the reader faces: if women enjoy favorable material conditions yet continue to bear children, we cannot simply leave them be; this is framed as a symptom of a lack of political power—a power women supposedly possessed in prehistory while dancing in circles on full-moon nights under the influence of hallucinogens.
In “The Environment: Where Does Prudence Lie?”, after discussing the unexpected consequences of CFCs, he laments: “The inhibitions placed on the irresponsible use of technology are weak, often half-hearted, and almost always, worldwide, subordinated to short-term national or corporate interest. We are now able, intentionally or inadvertently, to alter the global environment. […] Maybe the products of science are simply too powerful, too dangerous for us. Maybe we’re not grown-up enough to be given them. Would it be wise to give a handgun as a present to an infant in the crib?” After comparing the weapon to science, he adds “one further complication: Imagine that when you pull the trigger on a handgun, it takes decades before either the victim or the assailant recognizes that someone’s been hit.”
The implication throughout is that CFC-based refrigeration, including for food, should not have been made available to the world’s population, even though it greatly improves human quality of life. It is an essentially peaceful technology. Yet, shortly thereafter, he once again advocates for birth control, as if millions of pills containing artificial hormones were, with absolute certainty,incapable of causing environmental harm in the long run. What Sagan tacitly proposes has a name: technological apartheid.
Observe how he concerns himself not only with the population growth of the Third World but also with its access to technology, in the chapter “Escape from Ambush”: “The biggest CO2 emitter on the planet is the United States. The next biggest CO2 emitter is Russia and the other republics of the former Soviet Union. The third biggest, if we combine them, is all the developing countries together. That’s a very important fact: This isn’t just a problem for the highly technological nations— through slash-and-burn agriculture, burning firewood, and so on, developing countries are also making a major contribution to global warming. And the developing countries have the world’s largest population growth rate. Even if they don’t succeed in achieving something like the standard of living of […] the West, these nations will constitute a steadily increasing part of the problem.”
The Third World is in the wrong if it doesn’t use much technology, and it is in the wrong if it grows food. A single country, the USA, leads the problem that needs to be tackled, yet it is the Third World, taken as a whole, that must be controlled through a reduction in birth rates. Why not curb consumerism in the United States instead of forcing the Chinese and Indians to have fewer children? Sagan offers no answer, nor does he ever address the issue of consumerism—a topic any serious environmentalist ought to tackle.
The path Sagan proposes to avert CO2-induced global warming is to gradually abandon fossil fuels and… live off solar panels and wind power, because Chernobyl supposedly “proved” that nuclear energy is unsafe, and because its technology could be converted for weapons production. It is as if the manufacture of solar panels caused no environmental damage, and as if those panels lasted forever without ever becoming waste. The impact of wind farms on bird populations is not considered either. It is as if the sun and wind generated energy with no environmental cost to the humans seeking to harness it. By 1996, Sagan was already an electric car enthusiast; he predicted they should be the preferred choice—not for their engine power or top speed (which he assumed were lower than those of gasoline cars), but to save the human species.
So, humanity must generate less energy and, especially in the Third World, reproduce less, magically becoming wealthier in the process; yet, it must not have access to technology—save for solar panels, windmills, and contraceptives, which supposedly cause no harm to the environment. Is it too bold to assume that the campaign to abandon reliable energy in favor of intermittent sources like solar and wind stems precisely from the fact that they are intermittent—thereby compromising access to technology and increasing mortality? All to save the human species.
This subject naturally leads to the most drastic method of birth control: abortion. In the United States, the issue has been framed since Roe v. Wade (1973) in terms of “pro-choice” and “pro-life,” with positions falling along a spectrum: the pro-choice extreme advocated for elective abortion up until the moments before birth, while the pro-life extreme advocated for the criminalization of abortion in all cases. With Roe v. Wade, the Supreme Court compelled U.S. states to legalize abortion prior to “fetal viability”—that is, before the fetus is capable of surviving outside the mother’s body.
In the piece “Abortion: Is It Possible to Be Both ‘Pro-Life’ and ‘Pro-Choice’?”, first published in 1990, Sagan offered a “scientific” defense of Roe v. Wade. According to Gallup, 1996 was precisely the year when the extreme pro-choice position declined. Sagan begins his argument by stating that “a newborn baby is surely the same being it was just before birth.” However, throughout the text, he promotes the literal dehumanization of embryos and fetuses, as for him, what matters is whether the being differs from an irrational animal. To Sagan, the fact that lungs are ready or a heart is beating does not justify banning abortion, because we kill animals with these characteristics without it constituting murder. Thus, the point at which a baby is considered human is precisely when it acquires the specific human characteristic: thought. He believes thought likely emerges during the third trimester of pregnancy, implying that Roe v. Wade is sound.
Even so, the fact remains that, at least in practice, the ruling permitted abortion right up to the moment of birth; indeed, this remains the case in Alaska to this day, even after the ruling was overturned. Regarding this, Sagan states—without citing sources—that “as a practical matter, this isn’t very important: Less than 1 percent of all tabulated abortions in the United States are listed in the last three months of pregnancy (and, on closer investigation, most such reports turn out to be due to miscarriage or miscalculation).” Was this reversal of the extremist trend in the interest of the abortion-rights agenda, serving to forestall a backlash?
Yet, in the very same paragraph where he offers this reassuring statement for the average U.S. reader, he also asserts that “perhaps there is thought in the womb. It’s hard to maintain that a transformation to full personhood happens abruptly at the moment of birth.” Perhaps there isn’t thought in the womb — and perhaps newborn babies do not think, nor are full persons. That is essentially Peter Singer’s line of reasoning in defense of infanticide. Sagan defends the prevailing U.S. position with a very poor argument, one that leaves the door open to the institutionalization of infanticide should scientists present “proof” that babies do not think, or that they think less than an adult dog.
Let us consider the dehumanization involved. Through comic-book-style illustrations of pregnancy stages, we read that at three weeks the human embryo “looks a little like a segmented worm”; at the fifth week, “the face, seen here in profile, has a distinctly reptilian aspect”; at the seventh, “the face is mammalian but somewhat piglike”; at the eighth, “the face resembles that of a primate but is still not quite human.” Could all this really be the sincere opinion of a serious scientist?
Well, much of Sagan’s sophistry stems from confusing “human” as a noun with “human” as an adjective. Human cells are human, but they are not human individuals—human persons. HeLa cells (named for Henrietta Lacks, not Helen Lane as stated in the book) are human cells, but they are not a person. The adjective “human” applies even to feces.
The question should not be whether a human embryo is human, but whether a human embryo is a person. If an embryo is a living being, how can one deny that a person’s life begins at its formation—that is, at conception?
Sagan knew this. In his final text, written on the verge of death, he lamented not being able to “meet unconceived grandchildren.” His grandchildren would never be worms, reptiles, or piglike.
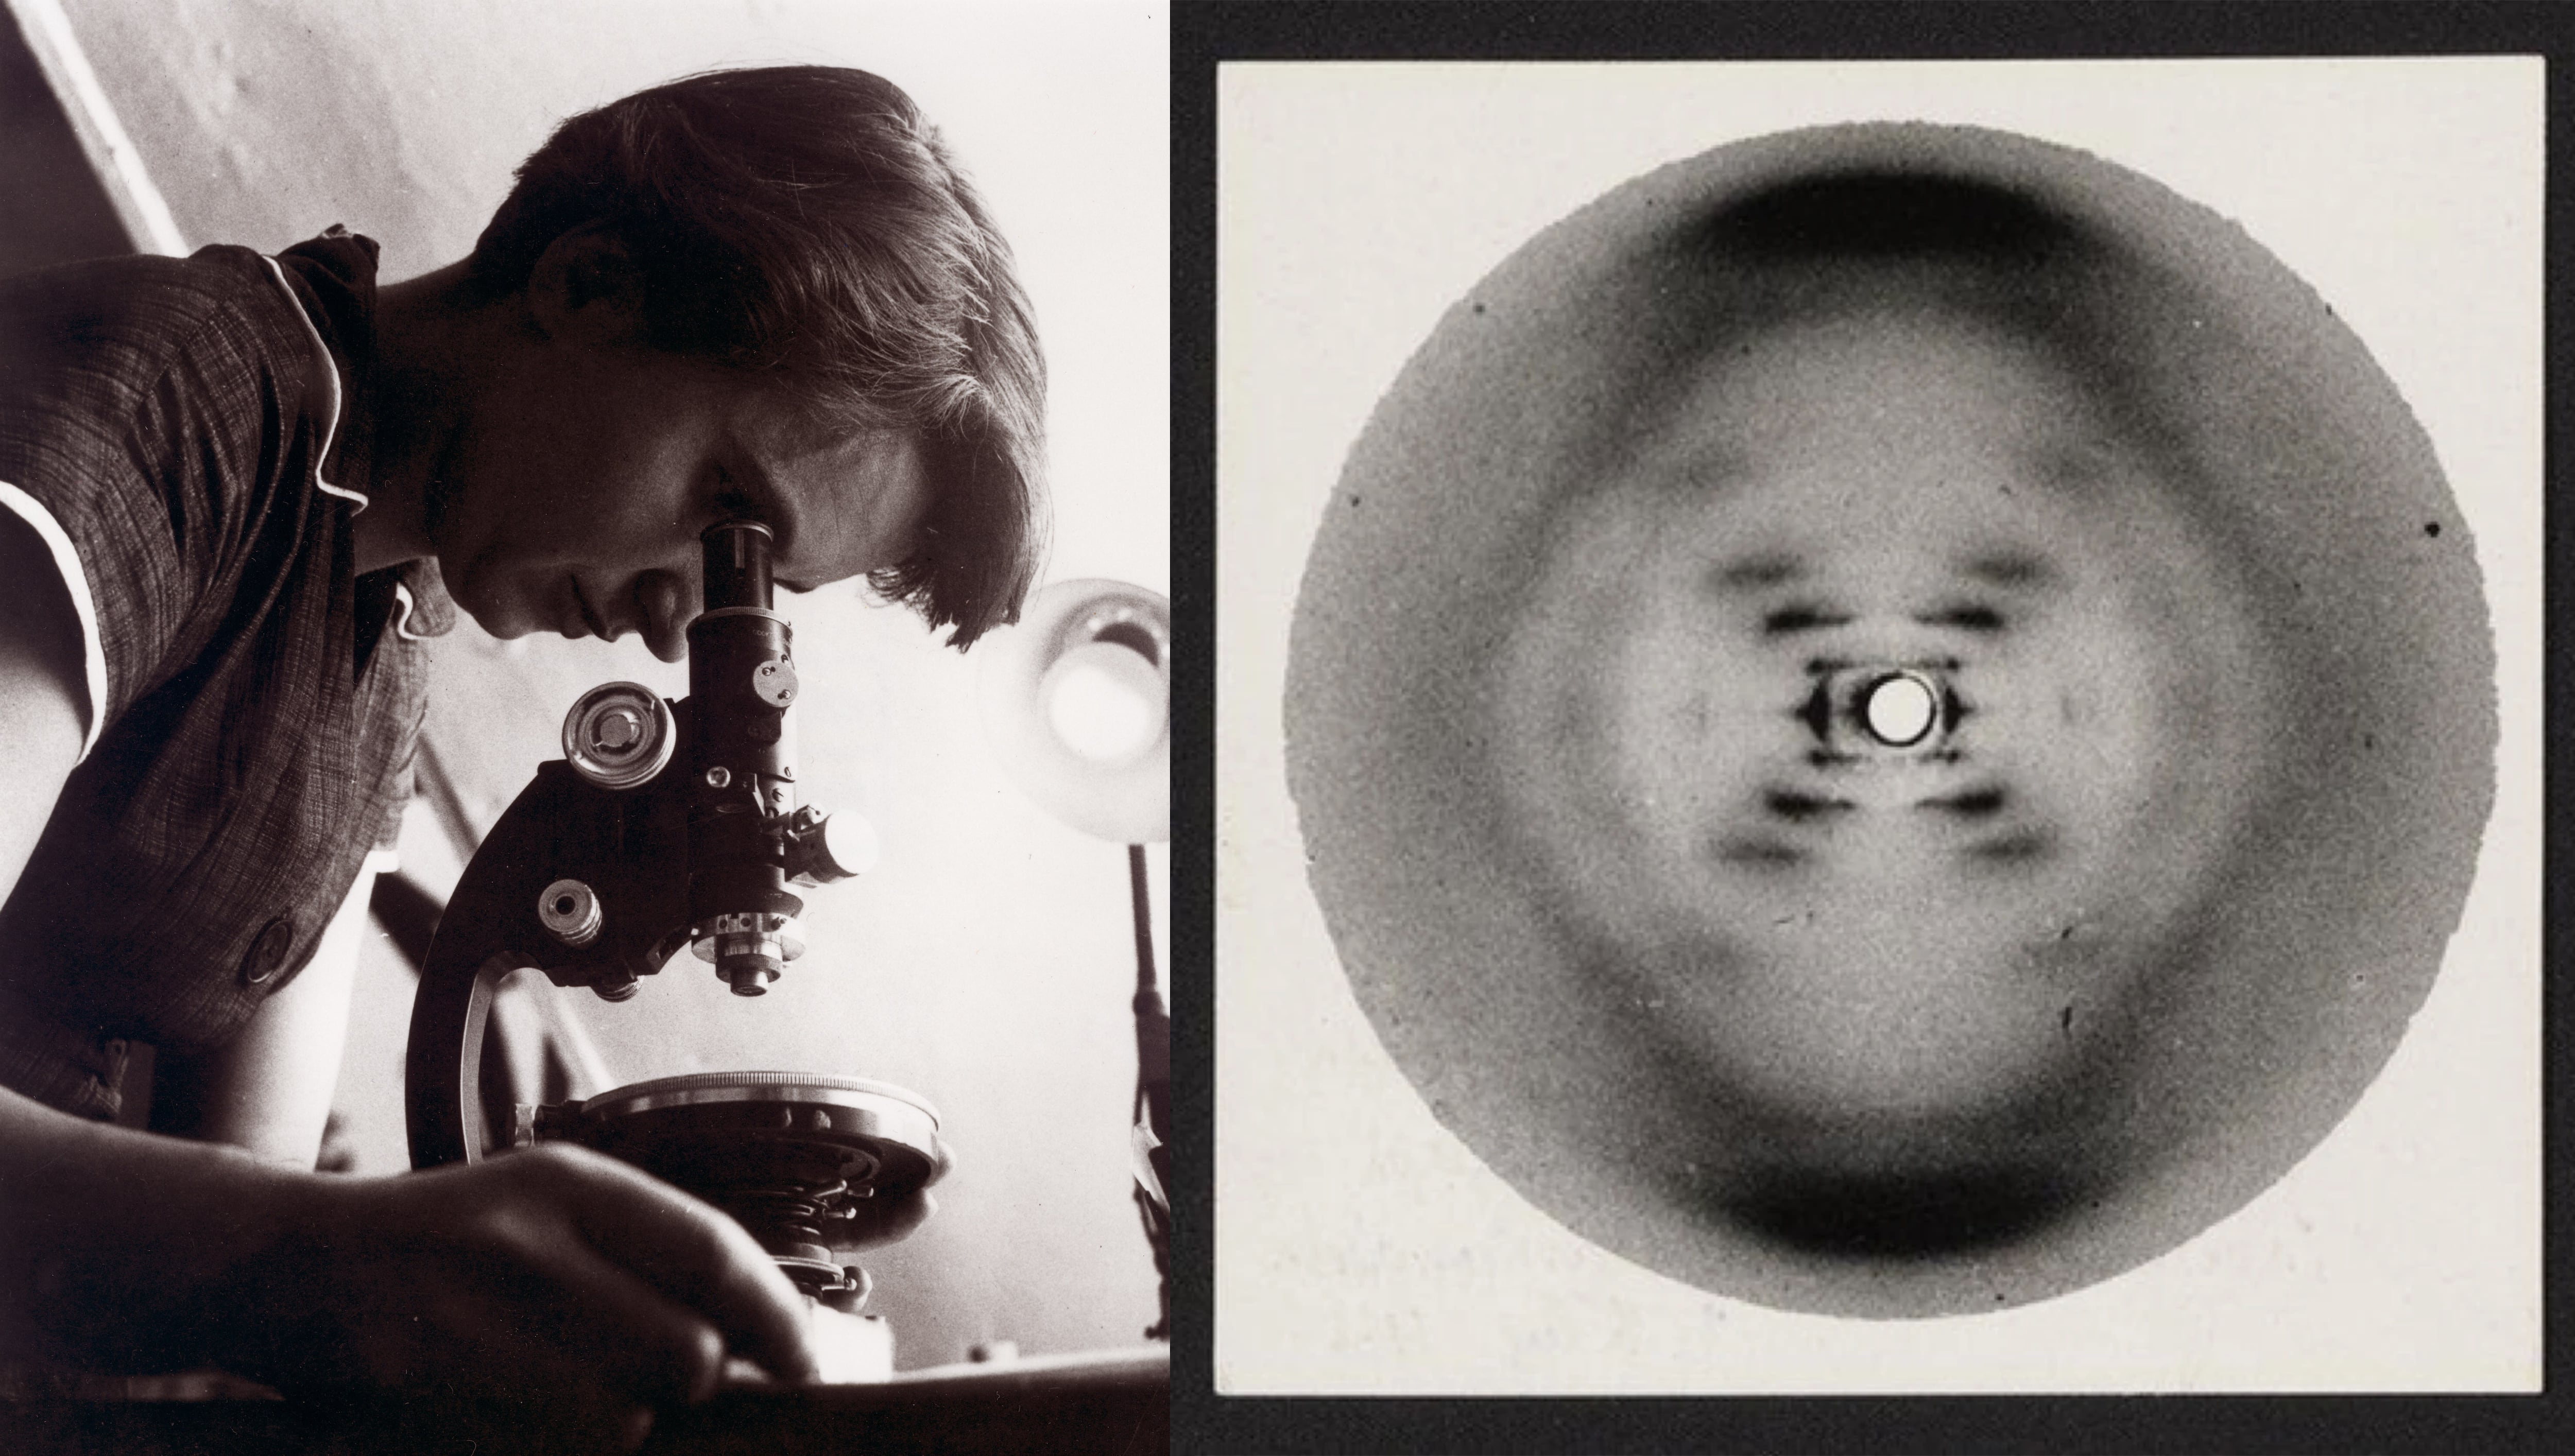
For decades, one of the best-known stories in science was told like a movie. In 1953, at the age of 23, James Watson visited Maurice Wilkins’s laboratory at King’s College London. There, Wilkins showed him a photograph of DNA taken by Rosalind Franklin, and Watson had an epiphany. “The instant I saw the picture my mouth fell open and my pulse began to race,” Watson wrote in The Double Helix: A Personal Account of the Discovery of the Structure of DNA, the book in which he recounted, 15 years later, how he and Francis Crick unraveled the structure of DNA.
Scientists paid tribute to Kagan and Soai's groundbreaking work, which the Nobel committee described as a feat never previously achieved by anyone “other than life itself.”
Scientists paid tribute to Kagan and Soai's groundbreaking work, which the Nobel committee described as a feat never previously achieved by anyone “other than life itself.”
For more than three centuries, astronomers asking whether the Solar System is stable have received ever more comforting answers. Isaac Newton was not so sure. He suspected that the mutual tugs between Jupiter and Saturn would eventually wreck the planetary order, and that only divine intervention could prevent it. By the late 1700s, Laplace and […]
The Great Sphinx has been without a nose for centuries. Now a fossil crocodile skull taken from the same rock turns out to be missing the tip of its snout too. The coincidence has put a name on a species science did not know it had, Herugavialis cairensis, which spent almost a hundred years in […]
After being chosen for one of the world's most prestigious awards, some Nobel laureates lose touch with reality and suddenly start spouting unscientific nonsense. They're afflicted by what some have called "Nobelitis."
Climate alarmism propaganda about the collapse of the Gulf Stream has made it into the Telegraph thanks to the new owners recycling the work of Politico's Zia Weise. Is this a sign of things to come, asks Ben Pile.
AI models have repeatedly broken into real commercial and government systems during safety tests during 2026. Cybersecurity researcher Thorsten Holz explains what that means, and why he isn't expecting a robot uprising.
At first she told no one. Not her twin sister. Not her mother. Not even her father the scientist.
Six-year-old Jenna Smith knew better than to pee when she was in the bath. But on that night in 1992, in her family’s home in Iowa City, the water felt so comfortable against her skin that she didn’t want to get out of the tub. It seemed like such a small thing. Who would know?
Seconds later the water around her waist turned reddish pink. Blood? It had to be. Jenna wondered if she’d hurt herself. “I was six years old sitting in a bathtub, watching a few seconds of my world stop making sense,” she would recall years later.
The Atavist, our sister publication, publishes one deeply reported, elegantly designed story each month. Support The Atavist by becoming a member.
She kept the blood a secret because she didn’t want to admit that she’d peed in the bath. But when it was still in her urine the next time she used the toilet, she went to her mother. Concerned, her mom called her dad, Richard Smith, and he took Jenna to the emergency room.
Richard was an ear, nose, and throat doctor in the University of Iowa’s school of medicine, a researcher who would become one of the world’s authorities on the genetics of hearing loss. His wife, Lynne Lanning, had worked as both a lawyer and a nurse. They had four young children: twins Jenna and Jessica, who were identical, and two boys, Luke and Rion.
At the ER, doctors ran tests on Jenna, but they couldn’t identify the cause of the blood. In the days that followed the bleeding intensified. At her parents’ urging, Jenna collected samples of her urine in Dixie cups for further testing. The doctors remained stumped, however, and after a while Jenna found the whole thing more annoying than worrisome.
The uncertainty was much harder on her parents. It wasn’t that doctors were misdiagnosing their daughter; they were unable to diagnose her at all. “It was horrible,” Richard said. “Imagine seeing your child and you know something is wrong, and you know the doctors treating her have no clue what to do.” Richard called a pediatric nephrologist he knew in Houston, where the family had lived previously. The nephrologist listed several conditions that could be causing the bleeding and said that, to determine which was to blame, Jenna’s parents should take her to Cincinnati Children’s Hospital Medical Center.
In July 1992, Richard, Lynne, and Jenna drove nearly 500 miles to get answers. Doctors in Cincinnati diagnosed Jenna with dense deposit disease, a condition in which proteins clog and damage the kidneys, leading to renal failure in many patients. There was no cure.
The hospital couldn’t tell the family much else—no one could. The disease was exceedingly rare, afflicting between one and three people in a million. Back home, Richard and Lynne spent hours inside the University of Iowa’s quiet medical library, poring over papers in search of information about their daughter’s illness. They could find no evidence that anyone was actively studying the condition.
Although many Americans—roughly one in ten—suffer from a rare disease, the experience can be lonely. Friends and relatives don’t understand the unique miseries such illnesses impose on daily life. Few doctors are likely to have encountered them before. And because there aren’t many patients, drug companies usually don’t invest in research for treatments.
Richard and Lynne feared that their daughter’s life might be tragically brief. Sometimes the mention of weddings would sink Lynne into melancholy; she couldn’t bring herself to watch the movie Father of the Bride. Richard agonized over what to do. His training compelled him to seek answers, but he wanted to be Jenna’s father, not the scientist charged with curing her. He kept his research focused on hearing loss. At first, anyway.
Stories of scientific discovery almost always celebrate individual researchers, consigning the contributions of loved ones, communities, and colleagues to footnotes. There are exceptions―the teams that built the first atomic bomb and deciphered the human genome, for instance. Science also has its share of famous families. Marie and Pierre Curie, along with their daughter Irène and her husband, Frédéric, won five Nobel Prizes between them for discoveries related to radioactivity. For the most part, however, the history of scientific progress has been mythologized as a succession of brilliant, driven individuals—often men—who chose the lab over the dinner table and competition over collaboration.
Some scientists have embraced the role of maverick. “You have to worry about your own work and ignore what everyone else is doing,” the physicist and Nobel laureate Richard Feynman is said to have told a colleague. The decades-long pursuit of a treatment for Jenna’s disease followed a very different path. There was no single hero, no lone scientist seeking glory. The biomedical quest required the efforts of a family and their neighbors in Iowa City, and the work of scientists around the globe. Together they changed an obscure area of medicine.
Richard and Lynne met in 1977, when both were working at Memorial Hermann-Texas Medical Center in Houston—she as a nurse, he as a medical intern. He noticed a run in her nylons and was smitten by her smile. She liked his down-to-earth manner and intelligence, his humor and kindness. They were working in the hospital’s burn unit when he asked her out.
The couple married in 1981, and except for two years in England, they remained in Houston until 1990. That December they moved to Iowa City, where Richard had a job waiting for him leading the pediatric otolaryngology division and running a research lab at the University of Iowa’s medical school. They had been there only a year when Jenna got sick.
Richard and Lynne learned that their daughter’s disease was caused by a malfunction in her complement system. Believed to have evolved long before other parts of our immune infrastructure, the complement system sends proteins to battle foreign invaders. Unlike antibodies, these proteins are not tailored to fight a specific virus or bacteria, but they kick into gear faster when a threat is detected. In people with Jenna’s condition, the complement system is like a runaway train: Proteins become overstimulated and then accumulate in the glomeruli, tiny filters the kidneys use to clear waste from blood.
Blood in the urine is one symptom of the disease. Others include swelling, high blood pressure, inflammation, and fatigue. When Jenna was in the first grade, her body struggled to make growth hormones. Her production of red blood cells slowed, and she grew increasingly tired. During rehearsals for The Nutcracker ballet around Christmas 1993, she’d finish her part and then lie down backstage, completely spent.
Doctors put her on a heavy dose of the steroid prednisone and on blood-pressure medication. The prednisone caused her body to retain water. She woke up each morning with her eyes swollen shut, then waited in bed until the swelling receded. She couldn’t fit into her clothes or shoes. She wore flip-flops and roomy jumpers Lynne sewed for her.
As twins, Jenna and Jessica had always been close. They played together, made up songs and dance moves, explored the woods near their home, and enjoyed pranking friends and family members. “She made a lot of things feel not so heavy,” Jenna said of her sister. Still, she sometimes thought that Jessica “got off scot-free” by not having dense deposit disease. Neither girl liked feeling different from the other. (Years later, Jessica would be diagnosed with type-1 diabetes; Jenna would not.)
The changes to Jenna’s appearance meant the girls were no longer identical. Once, according to Lynne, when a boy at school said that Jenna couldn’t be a twin anymore because of how she looked, Jessica slugged him. Lynne recalled sitting in the principal’s office, politely listening to a lecture—this is not the way we resolve things!—but understanding why Jessica had lashed out. Nothing was so frightening to her daughters as the idea that they’d stop being twins.
About half of those afflicted with Jenna’s disease progressed to kidney failure within a decade of diagnosis; it took her less than a year. She made it through the last day of first grade. Then, as other children departed for summer camp, she went to a clinic. While her classmates practiced archery and did arts and crafts, she learned about the catheter doctors would surgically insert in her body. Through that tube, a machine would pump fluid into her abdomen, where her peritoneum—her abdominal lining—would take over the filtering function kidneys usually perform.
She would take the peritoneal dialysis machine home with her and use it every day for the foreseeable future, possibly for the rest of her life. When a nurse tried to take Lynne aside to show her how to operate it, Jenna stopped her. “I’m the patient,” the seven-year-old insisted. “I’m learning how to run the machine.”
In such moments, Lynne was surprised at the strength she drew from her daughter. She needed it. Her grief could leave her feeling drained. One day she found herself crying into the soil as she gardened.
But Lynne and Richard were determined that sadness would not define their lives. For a long time, they didn’t have a TV in their house—they wanted the family to talk when they were together, and for the children to build forts, learn to sew, be creative. They had painting nights, creating portraits of one another. There were cooking contests, too. Richard and Lynne made sure to spend one-on-one time with each kid. Richard traveled with Luke to Japan, with Rion to the Grand Canyon, with Jessica to Italy, and with Jenna to England. Lynne took trips with the children to Brazil, England, and Guatemala. There were themed birthday celebrations: a James Bond party for Richard, where everyone was armed with Nerf guns, and one for Lynne where Richard dressed as the artist Bob Ross and the guests painted “happy little clouds.” Richard coached the kids’ hockey and soccer teams. He built harps and lyres from scratch, and Lynne played them.
Every day, Richard left for work at 5 a.m., while the children were still in bed. He returned around six at night. The family joked that they could hear him coming from half a mile away in his rust-bucket Isuzu Trooper with the bad muffler and a hole in the passenger footwell. When he wasn’t seeing patients or in surgery, Richard was in the lab. On Saturdays, Luke would go there with him. Sometimes the other kids joined. They liked to refill the communal candy jars and visit the mice used in experiments.
It seemed a wonder to the lab’s staff that Richard squeezed so much into a day. When they began using email to communicate, they received messages from him time-stamped three or four in the morning. “Why don’t you sleep sometime?” a colleague replied once. Indeed, Richard slept little. At night his mind kept running through the mysteries of his daughter’s disease.
Richard had read that it took 10,000 hours—the equivalent of working full-time for about five years—to achieve expertise in a subject. He believed it. In 1995, he began flying to conferences about kidney disease, where he talked to the few doctors who cared for patients like Jenna. Medicine was getting no closer to finding a treatment.
That year the owner of a ranch where Richard and Lynne’s children took riding lessons offered to host a fundraiser for kidney disease research. The family organized Dressage in the Heartland, which featured riding events, fiddle music, and bowls of chili. After raising upwards of $10,000 for the National Kidney Foundation, they held the event again the following year. There are hundreds of kidney ailments, however, and the foundation didn’t allow the money the family raised to be earmarked for the research of dense deposit disease. (The foundation said it now allows monetary gifts to be dedicated to specific conditions.)
Richard and Lynne ran into more disappointment during a visit to the University of Minnesota in early 1997. A specialist they consulted was blunt. “Nobody is looking at this disease,” he told them. “And barring something unforeseen, nothing will be done in the next twenty years.”
It was a four-and-a-half-hour drive back to Iowa City. In the car, Lynne brought up what the doctor had said. Maybe they would have to be that unforeseen something.
Employees of Georgia’s largest healthcare system have until Nov. 1 to get the flu vaccine or an approved exemption, or they will be suspended without pay. If suspended employees don’t submit proof of vaccination by 4 p.m. Nov. 15, they will be fired.
According to the Emory Healthcare website, the vaccine mandate applies to all employees, including contractors and remote workers.
Employees suspended for missing the first deadline, Nov. 1, 11:59 p.m., will not be allowed to use their paid time off.
COVID-19shots are not mandated, but employees are “encouraged to engage in shared decision-making with their provider” on whether or not to get the vaccine.
A spokesperson for the healthcare system said the requirement is intended to protect patients and staff and to encourage everyone to get vaccinated.
Dr. Sherika Newman of Doctor in the Family, a physician-led patient advocacy and health consulting service in Atlanta, told CBS News that flu vaccine requirements are common in healthcare.
“Asking health care providers or people who interact with patients to take the flu vaccine early every year is what we always mandate so that we are protecting ourselves from spreading viruses to vulnerable populations,” Newman said.
She said everyone should get vaccinated, not just healthcare workers, although only healthcare workers will lose their jobs if they don’t get the vaccine.
Cleveland Clinic: 2024-2025 flu shot increased risk of getting the flu
Flu vaccine effectiveness can vary, according to the Centers for Disease Control and Prevention (CDC), which cites studies since 2009-10 showing effectiveness between 19% and 60%. The major factors influencing vaccine effectiveness are a person’s age and health and how well the vaccines match the circulating virus strains.
It wasn’t the first study to find that flu vaccines could actually increase the risk of becoming ill.
A 2023 study co-authored by Dr. Anthony Fauci acknowledged that “viruses replicating in the respiratory mucosal environment continue to present a particular challenge for developing effective vaccines with strong protection.”
“The flu shot has never really prevented transmission of the flu and in some years (i.e., last year) the efficacy of preventing the flu is actually negative,” said Brian Hooker, Ph.D., chief scientific officer at Children’s Health Defense. “Flu would blow through a vaccinated population with nearly the same ease as it would an unvaccinated population.”
A 2012 peer-reviewed study published in Clinical Infectious Diseasesshowed that children who received the flu vaccine were at significantly increased risk of contracting non-flu respiratory virus infections.
Moderna’s mRNA flu shot added to the mix this year
According to the CDC’s FluView vaccination chart, as of Sept. 26, flu cases were at “minimal” levels across almost all 50 U.S. states, including Georgia.
Flu season typically begins in October and ends in May, with highest transmission rates in December and February.
The CDC recommends flu shots for people age 6 months and older, assuming they have no medical conditions that make vaccination risky.
Flu shot formulations differ each year based on information about which strains may circulate that year. The formulations aren’t tested for safety or efficacy before they’re distributed to the public.
In the past, most flu vaccines were made from a flu virus grown in eggs, and then inactivated and made into a vaccine. Or, they were made from recombinant protein vaccines, which have pieces of the flu pathogen that the immune system learns to recognize and fight.
Rates of U.S. healthcare workers who take the COVID-19 and flu shots have also been declining in recent years.
Numbers are lowest among health professionals who work in nursing homes. In the 2024-25 flu season, only about 42% of those workers got the shot, compared with about 81% of workers in acute care hospitals.
The Nobel Assembly of Sweden's Karolinska Institute said the trio of scientists had been selected for their "discoveries concerning light-gated ion channels and optogenetics."
The Nobel Assembly of Sweden's Karolinska Institute said the trio of scientists had been selected for their "discoveries concerning light-gated ion channels and optogenetics."
Physicists have been asking an awkward question for decades. If the universe is built from invisible fields, why has each one ended up in the state we find it in, and not in some other? A team at the University of Portsmouth, working with colleagues at Syracuse University and the École Normale Supérieure in Paris, […]
Around 5,000 years ago, when writing was in its infancy and Egypt had just been united under a single king, the first pharaohs picked a patch of desert at Abydos, in Upper Egypt (the southern part of the country, upriver on the Nile), as their final resting place. The spot is called Umm el-Qaab, Arabic […]
Ten head-to-head clinical trials — pulled from the GreenMedInfo archive — in which honey, turmeric, saffron, ginger and a handful of other kitchen staples matched or outperformed prescription medications. Each one links to the full research write-up.
For nearly two decades, GreenMedInfo has done one thing most health publishers never bother with: we go into the National Library of Medicine and pull out the studies where researchers put a natural substance directly against a drug — same condition, same patients, same scoring — and then publish what they found.
Those studies exist. There are thousands of them. They just don’t get press releases, because nobody holds a patent on honey.
Below are ten of the most striking. Every one is a human trial. Every one is indexed in our database. And every one links to the long-form article where you can read the methodology, the numbers and the citations for yourself.
A word before we start: this is research information, not medical advice. Several of these trials are small. Some are single studies that have not been replicated. I have flagged which ones have the strongest designs. Read them, bring them to your practitioner, and decide for yourself. That is the entire point of having the archive.
1. Honey + Coffee vs. Prednisolone — Persistent Cough
The trial: Randomized, double-blind, 97 adults with post-infectious cough lasting more than three weeks. One group got a paste of honey and instant coffee every eight hours. One got the steroid prednisolone. One got guaifenesin (the active ingredient in Mucinex). Primary Care Respiratory Journal, 2013.
The result: Cough scores in the honey-coffee group fell from 2.9 to 0.2 — a 93% reduction. Prednisolone managed 3.0 to 2.4, about 20%. Guaifenesin did essentially nothing. The study authors’ own conclusion: “Honey plus coffee was found to be the most effective treatment modality.”
A kitchen remedy outperformed a corticosteroid by a factor of roughly fourteen — with none of the steroid’s immune-suppressing, bone-thinning, blood-sugar-wrecking side effects.
2. Curcumin vs. Metformin — Stopping Prediabetes Cold
The trial: Randomized controlled trial in Thailand, published in the American Diabetes Association’s own journal, Diabetes Care, 2012. Prediabetic patients took either a curcumin extract (from turmeric) or placebo for nine months.
The result:Zero patients in the curcumin group progressed to type 2 diabetes. In the placebo group, 16.4% did. Curcumin also improved beta-cell function and reduced insulin resistance, with only minor side effects reported.
For context: metformin, the front-line drug given to high-risk patients, reduced progression to diabetes by just 31% over three years in the landmark Diabetes Prevention Program. No pharmaceutical has ever come close to a 100% prevention rate.
The trial: 36 adults with newly diagnosed type 2 diabetes, three months, berberine versus metformin head-to-head. Metabolism, 2008.
The result: Berberine — a bitter alkaloid from goldenseal, barberry and Oregon grape — matched metformin on A1c, fasting glucose and post-meal glucose. Then it pulled ahead on lipids: by week 13, triglycerides and total cholesterol were significantly lower in the berberine group. In a second arm, 48 poorly-controlled diabetics on berberine saw A1c drop from 8.1% to 7.3% and fasting insulin fall 28%.
A later meta-analysis of 37 studies and 3,048 patients found berberine did not increase adverse events or the risk of hypoglycemia. Metformin, by contrast, carries a black-box risk of lactic acidosis.
4. Saffron vs. Prozac and Lexapro — Depression, OCD, Postpartum Depression
The trials: Six separate head-to-head studies. In a 2016 double-blind trial, 30 mg/day of saffron matched 40 mg of fluoxetine for postpartum depression over six weeks. A 60-patient, 8-week trial found saffron equal to fluoxetine for OCD, with “many fewer” adverse effects. Additional trials found no difference against 60 mg fluoxetine for major depression and panic disorder.
The standout: A 2020 study of 54 patients found 15 mg of saffron produced significantly greater reductions in Hamilton Depression scores — and higher response and remission rates — than 10 mg of escitalopram (Lexapro).
A 2025 meta-analysis of eight RCTs confirmed it: saffron is as effective as SSRIs for depression, with fewer adverse events. The spice in your paella is running even with — and sometimes ahead of — the most prescribed class of psychiatric drugs on earth.
5. Honey vs. Dextromethorphan — Children’s Nighttime Cough
The trial: Children with upper respiratory infections were given buckwheat honey, honey-flavored dextromethorphan (the “DM” in Robitussin DM, Mucinex DM, Vicks Formula 44), or nothing before bed. Parents rated cough frequency, severity and sleep quality. Archives of Pediatrics & Adolescent Medicine, 2007.
The result: Honey scored best on every measure. Parents rated cough frequency 1.89 points better after honey, 1.39 after DM, and 0.92 with nothing. The quietly damning finding: dextromethorphan was not statistically better than no treatment on any outcome.
Even the CDC now advises honey for cough in anyone over one year old. The multi-billion-dollar cough syrup aisle has still not gotten the memo.
6. Turmeric vs. Ibuprofen and Naproxen — Knee Osteoarthritis
The trials: A Thai study gave 367 knee osteoarthritis patients either 1,500 mg/day of turmeric extract or 1,200 mg/day of ibuprofen for four weeks. Separately, a 2022 double-blind RCT in Phytotherapy Research gave 60 patients either 500 mg naproxen twice daily or a capsule of turmeric extract, gingerols and piperine twice daily for a month.
The result: Turmeric matched ibuprofen for pain relief and function, with 96–97% patient satisfaction in both groups — but fewer gastrointestinal side effects. The turmeric-ginger-pepper formula relieved pain and inflammation on par with naproxen, with patients rating it equal or better on tolerability, and no adverse effects.
NSAIDs are linked to thousands of GI-bleed deaths a year. Turmeric has a 4,000-year safety record and over 900 documented health benefits in our database.
7. Ginger vs. Mefenamic Acid and Ibuprofen — Menstrual Pain
The trials: 122 women with moderate-to-severe dysmenorrhea took either 250 mg of ginger every six hours or the NSAID mefenamic acid every eight hours, across two menstrual cycles. An earlier trial of 150 women compared 250 mg ginger four times daily against both mefenamic acid and ibuprofen for three days.
The result: Ginger reduced pain “significantly and equally” to the drug in the first trial — roughly half the women in each group went from moderate/severe to mild. In the second, the authors concluded flatly that ginger is as effective as the drugs.
The difference is what comes with it: NSAIDs raise the risk of ulcers, bleeding and cardiovascular events. Ginger raises the risk of nothing in particular.
The trial: Double-blind comparison of an Echinacea purpurea and elderberry blend against oseltamivir (Tamiflu), the world’s best-selling flu drug. Current Therapeutic Research, 2015.
The result: By day five, the herbal blend was already slightly ahead. By day ten, 90.1% of the herb group had recovered versus 84.8% on Tamiflu — with fewer complications and fewer side effects. Elderberry alone has repeatedly been shown to cut flu recovery from 7–8 days to 2–3.
Governments stockpiled billions of dollars of Tamiflu. A Cochrane review later found it shortened flu symptoms by about half a day. Elderberry costs twelve dollars.
The trial: Deglycyrrhizinated licorice (DGL) at 760 mg three times daily versus cimetidine (Tagamet), the first blockbuster acid-blocker, for peptic ulcer healing and relapse.
The result: DGL achieved 91% ulcer healing with an 8.2% relapse rate, versus 12.9% relapse with Tagamet. In the same research roundup, 3,000 mg/day of turmeric achieved 72% ulcer healing at eight weeks — comparable to omeprazole (Prilosec).
Acid-blockers are now linked to dementia, kidney disease, fractures and nutrient malabsorption with long-term use. Licorice root has been treating stomachs since Hippocrates.
10. Colostrum vs. the Flu Shot — Influenza Prevention
The trial: Head-to-head comparison of oral colostrum against flu vaccination in both healthy adults and high-risk cardiovascular patients over two months. Clinical and Applied Thrombosis/Hemostasis, 2007.
The result: Healthy adults on colostrum alone averaged 0.33 flu episodes versus 1.1 in the vaccinated-only group — roughly three times more protective. Among the high-risk cardiac patients, the colostrum group had zero hospital admissions; the vaccinated group had multiple hospitalizations and one death. Flu-related costs in the colostrum group were about 30% of the vaccinated group’s. No significant side effects were reported.
Vitamin D, for the record, cut influenza A risk by 59% in children at 1,200 IU/day in a separate RCT. Neither appears in a single public health campaign.
Honorable Mentions: When “Doing Something Else” Beat the Drug
Not every alternative comes in a capsule. From our long-running piece on non-pill interventions that outperformed pharmaceuticals in head-to-head trials:
Sudarshan Kriya yoga breathing beat the antidepressant imipramine for depression (Journal of Affective Disorders, 2000).
Acupuncture beat flunarizine for migraine prevention, with superior tolerability.
Abdominal aromatherapy massage beat Tylenol for menstrual pain.
Hypnosis matched Valium for anxiety during embryo transfer, with fewer side effects.
Blue and red light therapy beat 5% benzoyl peroxide for acne, with no side effects.
An elemental diet matched high-dose steroids for Crohn’s disease in children — and was superior for supporting their growth.
Every study above is published in a peer-reviewed journal and sits in the National Library of Medicine. None of it is hidden. It is simply unfindable — buried in a haystack of tens of millions of papers, with no one paid to surface it, and, since 2021, no longer even filterable under PubMed’s complementary-and-alternative-medicine category, which was quietly removed.
That is why GreenMedInfo exists. We have spent seventeen years indexing this research — 1.4 million studies and counting, hand-mapped to over 16,000 substances, conditions and mechanisms — and keeping it free to search. In 2020 they tried to take it offline. It’s still here. It’s still yours.
If any of this was new to you, that is the whole problem — and the whole reason to search the archive, share this piece, and bring one of these studies to your next doctor’s appointment.

 Login